Schizophrenia

Schizophrenia is a severe neuropsychiatric condition affecting about 27 million people worldwide1, characterized by hallucinations, delusions, disorganized thinking and profound cognitive impairment. Beyond dopamine, research implicates NMDA receptor hypofunction (underactive signaling at a receptor for the brain chemical glutamate) and inflammation. Nutrition has a supporting role: diet and activity reduce antipsychotic-associated weight gain2, and a few supplements have modest adjunct evidence3.

Neurological & Mental Health Evidence-Based

Last updated:

โš ๏ธ Medication safety: please read first. The nutrition and supplement approaches on this page are meant to work alongside your prescribed treatment, never to replace it. Never stop, reduce or change your antipsychotic medication without your prescriber's guidance. Doing so can be dangerous. Several supplements interact with antipsychotic medication4, so talk to your prescriber or pharmacist before starting anything on this page.

What Is Schizophrenia?

Schizophrenia is a chronic, severe mental disorder involving disruptions in thought, perception, emotional responsiveness and behavior. It manifests across three symptom domains: positive symptoms (psychosis, hallucinations, delusions, disorganized speech and behavior), negative symptoms (deficit states, flat affect, poverty of speech, anhedonia, avolition) and cognitive symptoms (impaired working memory, executive function, processing speed and attention) that persist even between psychotic episodes.

The exact causes are unknown5. The leading model involves dopamine, and medicines that lower its effect help many people. However, NMDA receptor hypofunction (glutamate hypothesis), inflammation and oxidative stress are also under study; whether nutrition can change them in a clinically meaningful way is not established3.

Studies report differences in gut microbiome composition and higher rates of some nutritional deficiencies, including vitamin D, in schizophrenia3. Whether these drive symptoms is not established.

โš ๏ธ Critical Note: Schizophrenia is a serious psychiatric condition requiring professional diagnosis and antipsychotic treatment6. Sudden discontinuation of antipsychotic medication significantly increases relapse risk. The nutritional strategies described here are add-ons, not replacements for psychiatric medication or therapy. Always implement with the knowledge and supervision of a qualified psychiatrist.
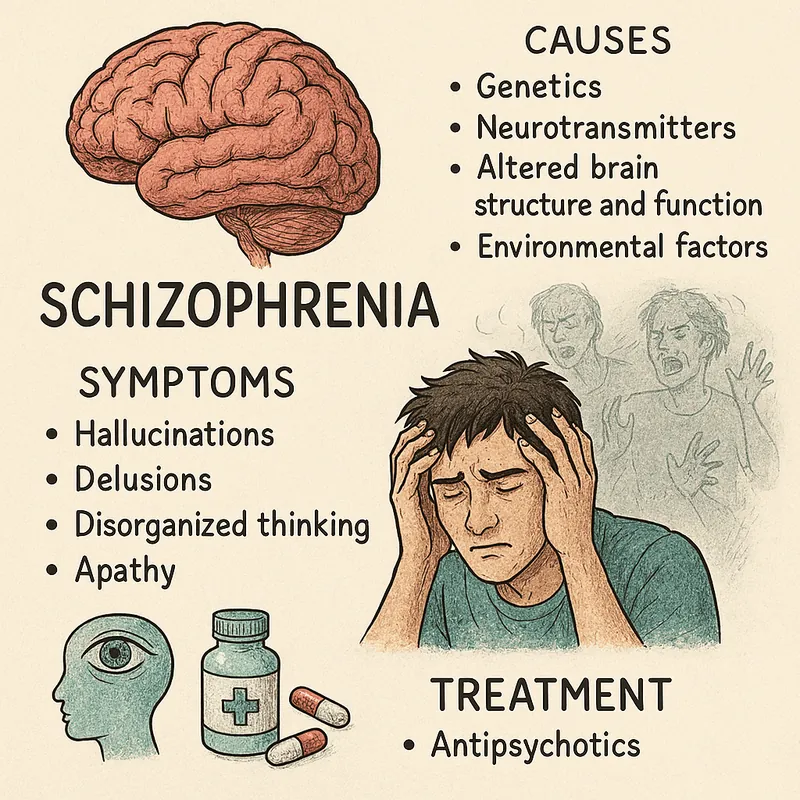
A calm head in profile with the brain, between a panel of symptoms (hallucinations, delusions, disorganized thinking and apathy) and a panel of causes (genetics, neurotransmitters, brain structure and function, and environmental factors), with antipsychotics named as the treatment

The Three Symptom Domains

Positive Symptoms (Added experiences)
Hallucinations, delusions, disorganized speech, disorganized or catatonic behavior
Negative Symptoms (Removed abilities)
Flat affect, alogia, avolition, anhedonia, asociality
Cognitive Symptoms (Impaired function)
Working memory, executive function, processing speed, attention, verbal memory. Together they are the strongest predictor of functional outcomes

Clinical Presentations on the Schizophrenia Spectrum

๐Ÿ”Š Paranoid Presentation

Dominated by prominent hallucinations and delusions, typically paranoid in content (beliefs of persecution, reference, grandiosity or special mission). Auditory hallucinations (hearing voices, often commenting on behavior, giving commands or conversing among themselves) are the most common and distressing symptom. This presentation generally carries a better prognosis than other forms, as it often responds more fully to antipsychotic medication.

๐ŸŒ€ Disorganized Presentation

Characterized by prominent disorganization of thought (derailment, tangentiality, word salad, loosening of associations), grossly disorganized behavior, and flat or inappropriate affect. Hallucinations and delusions may be present but are fragmented and less systematized than in paranoid presentations. Typically has a more chronic, treatment-resistant course with greater negative and cognitive symptom burden. Self-care deficits (nutrition, hygiene, medication adherence) are significant challenges.

โšก First-Episode & Early Psychosis

The period of untreated psychosis (DUP, duration of untreated psychosis) is a critical prognostic variable: longer DUP correlates with worse outcomes. Starting treatment as soon as possible after a first episode is an important step toward recovery7. One small trial reported fewer transitions to psychosis after omega-⁠3 in the prodrome8, and a larger trial designed to replicate it found no difference from placebo9, so this is not a reason to delay assessment or treatment.

Schizophrenia by the Numbers

27M
people worldwide living with schizophrenia, about 1 in 300 (WHO)1
15 to 20 years
the typical reduction in life expectancy, with cardiovascular disease the leading cause of death10
Possibly lower
red blood cell omega-⁠3 levels in people with schizophrenia than in people without it, suggested by a meta-analysis of 18 studies, though results varied widely and what that means for treatment is unsettled11
Not replicated
omega-⁠3 in the prodrome: one 81-⁠person trial found fewer transitions to psychosis (2010)8, and the larger 304-⁠person NEURAPRO trial found no difference from placebo9
2 in 3
people with psychosis worldwide do not receive specialist mental health care1
4.9%
of people with schizophrenia die by suicide, with the highest risk early in the illness; in the US, call or text 988 in a crisis12

Symptoms of Schizophrenia

Symptoms fall into three groups: psychotic (positive), negative and cognitive7.

SymptomWhat happens
Positive Symptoms
Auditory HallucinationsThe most common hallucination13. Voices are perceived as entirely real and external, not imagined. They may describe the person's actions, give instructions or talk among themselves. The distress and functional impairment depend on voice content, frequency and the person's relationship to the voices.
DelusionsFixed, false beliefs held with complete conviction, impervious to contradictory evidence. Most common: persecutory delusions (being watched, followed or targeted by a person, organization or supernatural force), referential delusions (believing TV, radio or strangers' comments are directed personally at them), grandiose delusions (belief in special powers or unique identity) and somatic delusions (belief in bodily changes or infestation). Insight into illness is often impaired.
Disorganized Speech & BehaviorThought disorder manifests as speech: derailment (rapid shifting between loosely associated topics), tangentiality (never reaching the conversational point), circumstantiality (excessive irrelevant detail) and, in severe form, word salad (incomprehensible speech). Disorganized behavior includes inappropriate emotional responses, unpredictable agitation, childlike silliness, poor goal-directed behavior, and neglect of hygiene and self-care. Catatonia (psychomotor immobility, waxy flexibility, echolalia) can occur in severe episodes.
Negative & Cognitive Symptoms
Flat Affect & Emotional BluntingReduced emotional expression, flat or blunted facial expression, monotone voice, decreased emotional responsiveness and reduced eye contact. The internal emotional experience may remain intact (the person still feels emotions), but the outward expression is severely diminished. Flat affect is frequently worsened by antipsychotic medications (dopamine blockade reduces emotional reactivity), which is worth raising with the prescriber.
Avolition & AnhedoniaAvolition (loss of motivation and goal-directed activity) and anhedonia (inability to experience pleasure from previously enjoyed activities) are the negative symptoms most responsible for functional disability. NAC has trial evidence for negative symptoms as an addition to medication, not as a replacement for it, and the omega-⁠3 evidence is weaker still.
Cognitive ImpairmentDeficits span working memory, processing speed, verbal memory, executive function (planning, cognitive flexibility, impulse control) and sustained attention. Cognitive symptoms are the strongest predictor of functional outcome (employment, independent living, social relationships) and the domain most resistant to antipsychotic treatment. In pooled trials, NAC improved working memory14; evidence for other supplements on cognition is limited3.
Metabolic & Physical Health ConsequencesPeople with schizophrenia die 15 to 20 years earlier than the general population, primarily from cardiovascular disease, not suicide10. This premature mortality is driven by antipsychotic-induced metabolic syndrome2 (weight gain, dyslipidemia, insulin resistance, diabetes, especially clozapine and olanzapine), high smoking rates, physical inactivity, poor diet and reduced healthcare access.

Causes of Schizophrenia

The exact causes are unknown: a mix of genes and environment makes some people more vulnerable, and stress or drugs can then trigger an episode5.

CauseHow It Contributes to SchizophreniaWhat Helps
Genes and family historyIt runs in families through many genes, none enough alone: when one identical twin has it, the other has a 1 in 2 chance, against a lifetime chance of about 1 in 100 in the general population5Knowing the family history helps early recognition; starting treatment soon after a first episode is an important step toward recovery7
Brain chemistry and developmentSubtle differences in brain structure (some arising before birth) and in brain chemicals such as dopamine; birth complications such as low birthweight, premature labor or lack of oxygen are more common in people who develop it5Antipsychotic medicine, which blocks the effect of dopamine or other brain chemicals, chosen and monitored with your psychiatrist15
Cannabis and other drugsHeavy cannabis use is linked with a higher risk1; regular use in the teens and early adulthood carries more risk, as do stronger forms; in people who have had psychosis, drugs can cause relapse5The diet section's advice to avoid alcohol and cannabis, and help to stop as part of treatment
Stress and life eventsBereavement, losing a job or home, the end of a relationship or abuse do not cause it but can trigger it in someone already vulnerable5; poverty and stressful surroundings are among the environmental factors studied7Psychosocial treatment such as CBT, skills training and family support alongside medicine; people in regular psychosocial treatment are less likely to relapse or be hospitalized7
Stopping medicine (relapse)Stopping antipsychotics can bring symptoms back15; maintenance treatment lowers relapse compared with stopping6Staying on treatment, with long-acting injections for some people6; any change only with your psychiatrist
Inflammation and gut bacteria (under study)CRP is moderately raised on average whether or not antipsychotics are taken16, and gut bacteria differ in a pattern shared with depression and bipolar disorder17; neither is shown to cause itNo diet or supplement on this page has been shown to work through these; add-on NAC has modest evidence for symptoms14

How Schizophrenia Is Diagnosed

Schizophrenia is diagnosed clinically using DSM-⁠5 criteria. Standard blood tests can identify deficiencies worth correcting, such as low vitamin D3, and monitor metabolic health2.

TestWhat it shows
Clinical Assessment Tools
PANSS (Positive and Negative Syndrome Scale)The gold-standard rating scale for schizophrenia severity, comprising 30 items across three subscales: Positive Symptoms (7 items: delusions, hallucinations, conceptual disorganization, etc.), Negative Symptoms (7 items: flat affect, alogia, avolition, etc.) and General Psychopathology (16 items: anxiety, depression, impulse control, cognitive, social). PANSS is the standard scale in drug and supplement trials.
Cognitive Assessment (BACS, MATRICS)The Brief Assessment of Cognition in Schizophrenia (BACS) and the MATRICS Consensus Cognitive Battery measure the seven cognitive domains most impaired in schizophrenia: speed of processing, attention/​vigilance, working memory, verbal learning, visual learning, reasoning/​problem solving and social cognition. A baseline lets changes be tracked over time.
Metabolic MonitoringAbout 1 in 3 people with severe mental illness had metabolic syndrome in a meta-analysis of 198 studies, with the risk varying between antipsychotics18. Essential monitoring: fasting glucose and HbA1c, fasting insulin (HOMA-IR for insulin resistance), complete lipid panel, blood pressure and waist circumference, every 3 to 6 months. Identifying and treating antipsychotic-induced metabolic syndrome with diet, physical activity and, where prescribed, metformin addresses the main driver of premature death in schizophrenia102.
Nutritional & Functional Lab Panel
Omega-⁠3 Index & Phospholipid ProfileThe Omega-⁠3 Index (EPA + DHA as % of red blood cell fatty acids) is reported lower in schizophrenia in some studies, though what that means for treatment is unsettled. It is a research measure, not a routine test in schizophrenia care.
Comprehensive Nutritional PanelVitamin D (25-⁠OH-D) where deficiency is suspected (it is common in schizophrenia and worth correcting3), serum zinc, RBC folate + active B12 (holotranscobalamin), homocysteine (higher on average in schizophrenia19), magnesium, iron studies (ferritin, TIBC) and vitamin C if intake is poor.
Inflammatory & Immune Markershs-CRP (moderately raised on average in schizophrenia whether or not antipsychotics are taken, in step with positive symptoms16) and celiac disease serology where symptoms suggest it.

Conventional and Holistic Treatment for Schizophrenia

๐ŸŒฟ HOLISTIC
๐Ÿ’Š CONVENTIONAL
๐ŸŒฟ

Holistic / Functional Approach

Omega-⁠3 EPA, NAC, glycine, sarcosine, folate, B12, zinc, vitamin D, anti-inflammatory Mediterranean diet

Omega-⁠3 Evidence
One small trial in people at ultra-high risk reported fewer transitions to psychosis8, but a larger trial designed to replicate it found no difference from placebo9; evidence in established illness is weak3
NAC Evidence
In a meta-analysis of seven randomized trials, NAC added to standard treatment improved negative and total symptom scores after 24 weeks, and working memory14
Glycine / Sarcosine
Glycine (an NMDA co-agonist) and sarcosine (which raises glycine) have small trials as add-ons to medication; sarcosine should not be combined with clozapine3, and glycine should be added to clozapine only with your psychiatrist's agreement34
Timeline
Adjunct effects are slow: in pooled trials, NAC's benefit appeared only at 24 weeks or later14; other adjuncts rest on small, mixed trials3

Full Holistic Approach Includes

  • N-Acetyl Cysteine (NAC, amount set by your prescriber), a glutathione precursor; in pooled trials it modestly improved negative and total symptom scores after 24 weeks as an add-on to medication14
  • Folate + B12: elevated homocysteine is reported more often in schizophrenia; folate and B12 lower it, and in one small crossover trial, folic acid, B12 and B6 improved symptom scores in people with raised homocysteine19
  • Probiotics (targeted strains): in a 14-⁠week randomized trial in schizophrenia, these strains made no significant difference to symptom scores, though fewer people developed severe bowel difficulty20
โš ๏ธ Integration note: Nutritional strategies add to antipsychotic medication; they do not replace it. NAC has the most consistent adjunct evidence, and it is modest14; omega-⁠3 results are mixed3. Diet and activity, rather than supplements, are what reduce antipsychotic-associated weight gain2. Niacin (orthomolecular therapy), tried in the 1950s and 1960s, is not a recommended treatment: later controlled studies did not confirm benefit35, and high-dose niacin can stress the liver. Discuss any supplement with your psychiatrist first.

Evidence-Based Supplements for Schizophrenia

These supplements have been tested in schizophrenia in mostly small trials, with modest or mixed results3. All are add-ons to antipsychotic medication and psychiatric care, never a replacement.

SupplementWhat it is forTypical rangeTimingNotes & cautions
Omega-⁠3 EPA (dominant)Evidence for omega-⁠3 is mixed, with some signal in early psychosis and little in established illness3. A small trial in ultra-high-risk youth reported fewer transitions to psychosis, still seen at follow-up a median of 6.7 years later26, but a larger 304-⁠person trial designed to replicate it found no difference from placebo9.EPA daily, amount set by your prescriber (use an EPA-dominant formula, EPA:DHA โ‰ฅ 2:1)With the largest meal of the day; fat improves absorptionRefrigerate after opening and choose a product with third-party testing. If you take a blood thinner, tell the clinician who manages it before starting, as INR checks may be needed27. In heart trials, fish oil supplements raised the risk of atrial fibrillation, an irregular heartbeat, more so at higher doses28, so agree on the amount with your prescriber first.
N-Acetyl Cysteine (NAC)NAC is a precursor of glutathione, an antioxidant reported lower in the brain in some imaging studies. In pooled randomized trials, NAC added to standard treatment improved negative and total symptom scores after 24 weeks, and working memory14.Amount set by your prescriber, in 2 divided dosesAway from meals for best absorption; morning and evening dosesYour prescriber can advise on starting slowly to limit mild nausea or loose stools. In trials, effects appeared only after 24 weeks or more14, so do not judge it early.
GlycineGlycine is a co-agonist at the NMDA receptor, which the glutamate hypothesis proposes is underactive in schizophrenia. Small randomized trials reported benefit for negative symptoms when glycine was added to antipsychotics3. High doses required due to glycine transporter competition.Amount set by your prescriber, in 3 to 4 divided doses (start low and increase weekly, as your prescriber directs)With meals to improve tolerance; divide doses throughout the day to maintain consistent synaptic glycine levelsThe very large amounts needed are the main limitation; your prescriber sets them. Sarcosine (see below) achieves similar NMDA enhancement at much lower doses and may be preferable. Do not combine sarcosine with clozapine3, and do not add glycine to clozapine without your psychiatrist, as glycine may blunt clozapine's benefit34.
Sarcosine (N-methylglycine)Sarcosine blocks the reuptake of glycine, raising its level at the NMDA receptor. Small randomized trials in Taiwan reported symptom improvements when sarcosine was added to antipsychotics other than clozapine3. The evidence remains limited.Amount set by your prescriberWith meals; morning and eveningMuch better tolerated than high-dose glycine. Discuss product quality with your psychiatrist. Do not combine with clozapine. Monitor for any changes in psychiatric symptoms when introducing; start at the amount your prescriber sets and increase it at 1 week if tolerated, as they direct. Tell your psychiatrist before starting it.
Methylfolate + Methylcobalamin (B12)Homocysteine is higher on average in schizophrenia. In a crossover trial in 42 people with raised homocysteine, a combination of folic acid, B12 and B6 lowered it and improved symptom scores compared with placebo19.Folate and methylcobalamin B12, amounts set by your prescriber (based on folate, B12 and homocysteine levels)Morning with breakfastYour prescriber may check homocysteine, B12 and folate first; MTHFR genetic testing is not recommended for this. If starting methylfolate causes increased anxiety or agitation, tell your prescriber. Recheck homocysteine after 3 months of supplementation.
Vitamin D3Vitamin D receptors are expressed throughout the limbic system and prefrontal cortex, the primary circuits disrupted in schizophrenia. A meta-analysis of 19 studies found lower vitamin D levels in schizophrenia, with about two-thirds of patients deficient29. Trials are small, and one placebo-controlled trial in people with low vitamin D found no effect on psychotic symptoms29.Amount set by your prescriber; most adults need no blood test firstWith the largest fat-containing meal of the day (fat-soluble)Higher body weight (antipsychotic-induced weight gain) requires higher doses. It is often combined with K2 MK-⁠7; K2 is involved in how the body uses calcium, though supplement benefits for bone and arteries are not established. If you take warfarin, clear any vitamin K supplement with the clinician managing your anticoagulation before starting or stopping it: vitamin K antagonizes warfarin, and changing your intake destabilizes the INR. Consistency matters more than avoidance. This does not apply in the same way to direct oral anticoagulants such as apixaban or rivaroxaban, but tell your prescriber about any supplement you take.
Zinc (Picolinate)Zinc is involved in brain signaling, including at NMDA receptors, and is part of over 300 enzymes. Zinc deficiency is reported in schizophrenia. In a 6-⁠week placebo-controlled trial in 30 inpatients, zinc added to an antipsychotic improved symptom scores30.Elemental zinc (as picolinate), amount set by your prescriberWith food, prevents nausea; evening preferredMeasure serum zinc; copper:zinc ratio targets are not an established clinical tool. High-dose zinc depletes copper further, so monitor with repeat testing at 3 months. Zinc picolinate is the best-absorbed form. Do not take within 2 hours of thyroid medication.

What to Expect Over Time

Treatment aims to ease symptoms, protect day-to-day functioning and support personal goals, with medicine and psychosocial care together7.

Treatment and supportive care, together
First Weeks

Antipsychotics can ease anxiety or agitation within hours, but hallucinations and delusions take days to weeks15. A first episode should lead to an early intervention team15. Weight, blood sugar and lipids are checked at the start10.

Months 1 to 3

If a medicine has not helped after several weeks of regular use, another can be tried15. Talking therapies such as CBT and family therapy work best combined with medicine15. Report side effects rather than stopping.

Months 3 to 12

The care plan should include healthy eating, physical activity and help to stop smoking15; diet and activity are what reduce antipsychotic weight gain2. Add-on NAC, if your psychiatrist agrees, showed benefit only after about 24 weeks14.

Long Term

Most people take medicine for 1 or 2 years after a first episode (longer if it recurs); stopping can bring relapse15; regular psychosocial treatment makes relapse and hospital stays less likely7. Medicine is reviewed at least yearly.

When to Seek Care

Thoughts of suicide or self-harm, or a plan: call or text 988 in the US, or 911 if a life is in danger7; in the UK call 111 or Samaritans on 116 123, or 999 31. Psychosis where someone cannot keep themselves or others safe is an emergency: call 911 or 999 or go to the emergency department31. On clozapine, call your doctor at once for fever, sore throat or other signs of infection, constipation or stomach pain, or fever with confusion or severe muscle stiffness32.

📬

Get new guides in your inbox. Once a month: new condition guides and research updates, including the trials that did not work. Free, no spam, and you can unsubscribe in one click.

Sign up

Medicine First, Nutrition Alongside

Omega-⁠3 EPA, NAC, sarcosine, vitamin D, zinc and folate have each been studied as additions to treatment. The adjunct evidence is modest and strongest for NAC14, and diet and activity are what reduce antipsychotic-associated weight gain2. Nutrition is not an alternative to psychiatric care; its clearest role is protecting physical health alongside it.

References & Evidence Notes

Each numbered entry below is either a source you can follow or a note setting out what the evidence does and does not support. Both are numbered together so the markers in the text line up.

Last reviewed October 20, 2026. Supplement entries are cross-checked against the NIH National Center for Complementary and Integrative Health and the Linus Pauling Institute Micronutrient Information Center.33 Never stop or reduce antipsychotic medication without your prescriber. Discontinuation is the single largest cause of relapse, each relapse carries risk and can leave lasting functional loss, and the decision to reduce is one that can be made carefully and slowly with a psychiatrist rather than unilaterally. Two further points that get overlooked. People with schizophrenia die considerably earlier than the general population, and the main cause is cardiovascular disease, not suicide, driven substantially by antipsychotic-induced metabolic effects and smoking. That is precisely where nutrition earns its place, and it is real work. And St. John's wort and several supplements interact with antipsychotics, so tell your prescriber what you are taking.

  1. On how common it is and what helps: WHO estimates that schizophrenia affects about 1 in 300 people worldwide, 27 million, that more than two out of three people with psychosis do not receive specialist mental health care, that heavy cannabis use is associated with a higher risk, and that effective care includes medication, psychoeducation, family interventions, cognitive-behavioral therapy and psychosocial rehabilitation, WHO, schizophrenia. ↩
  2. On metabolic management, where nutrition does the most good: dietary intervention and physical activity reduce antipsychotic-associated weight gain, and metformin has trial evidence for the same purpose. Addressing this early matters more than addressing it after ten years of weight gain, and it does not require stopping the medication causing it. ↩
  3. On nutritional adjuncts with evidence: omega-⁠3 fatty acids have shown mixed results, with some signal in early psychosis and little in established illness. N-acetylcysteine has modest evidence for negative symptoms. Vitamin D deficiency is common and worth correcting. Glycine and sarcosine target NMDA receptor function with small trials, and sarcosine should not be combined with clozapine. None is monotherapy. ↩
  4. On supplement interactions: St. John's wort induces cytochrome P450 3A4 and can reduce antipsychotic levels, risking relapse. Induction is measurable in healthy volunteers even at the lowest dose tested, PubMed 39152679, and reviews of herb-drug interactions in psychiatric practice list it among the products with clinically relevant effects on these medicines, PubMed 34370637. Caffeine affects clozapine levels; smoking induces CYP1A2 so that stopping smoking can raise clozapine levels significantly and requires dose review. These are real, documented interactions and they are why the supplement list belongs with the prescriber. ↩
  5. On causes: NHS guidance states that the exact causes are unknown; that schizophrenia runs in families without any single gene being responsible, the other identical twin having a 1 in 2 chance and the general population about 1 in 100; that subtle brain differences, differences in brain chemicals such as dopamine and birth complications are more common; and that stressful life events and drugs, especially regular cannabis use in young people, can trigger it in someone already vulnerable, and can cause relapse, NHS, causes of schizophrenia. ↩
  6. On treatment: antipsychotic medication is the foundation of treatment, and maintenance therapy substantially reduces relapse compared with discontinuation. Long-acting injectable formulations improve adherence and outcomes for many. Psychosocial treatments including cognitive behavioral therapy for psychosis, family intervention and supported employment add meaningfully on top of medication. ↩
  7. On symptoms, causes and treatment: NIMH guidance describes psychotic, negative and cognitive symptoms, says that several genes and environmental factors such as poverty, stressful surroundings and problems before birth may contribute, that starting treatment soon after a first episode is an important step toward recovery, that psychosocial treatment used with antipsychotic medication makes relapse and hospital stays less likely, and advises calling or texting 988 for thoughts of suicide and 911 in life-threatening situations, NIMH, schizophrenia. ↩
  8. On the first omega-⁠3 prevention trial: in a randomized trial of 81 young people aged 13 to 25 at ultra-high risk of psychosis in Vienna, given omega-⁠3 or placebo for 12 weeks, 2 of 41 in the omega-⁠3 group and 11 of 40 in the placebo group had developed a psychotic disorder by 12 months, PubMed 20124114. ↩
  9. On the replication trial: NEURAPRO randomized 304 young people at ultra-high risk of psychosis in 10 early psychosis services to omega-⁠3 or placebo, both with psychosocial care, and found no difference in transition to psychosis at 6 or 12 months; the authors concluded it clearly failed to replicate the original single-center trial, PubMed 27893018. ↩
  10. On premature mortality: life expectancy is reduced by roughly 15 to 20 years; a Romanian cohort of 635 patients followed for 10 years found a 17-⁠year reduction, with cardiovascular disease the leading cause of death, ahead of violent causes including suicide, PubMed 40883322. Drivers include antipsychotic-associated weight gain, dyslipidemia and diabetes, very high smoking rates, physical inactivity and inequitable access to physical healthcare. Metabolic monitoring at baseline and regularly thereafter is standard and is frequently not done. ↩
  11. On omega-⁠3 levels: a meta-analysis of 18 studies comparing the red blood cell membranes of 642 people with schizophrenia and 574 controls found suggestive evidence of lower levels of the omega-⁠3 fats DHA and DPA, both in people taking antipsychotic medicine and in those who had never taken it, and advised caution because results varied widely between studies, PubMed 23068078. ↩
  12. On suicide: NIMH estimates that 4.9% of people with schizophrenia die by suicide, a rate far greater than in the general population, with the highest risk in the early stages of illness, NIMH, schizophrenia statistics. ↩
  13. On symptoms: NHS guidance lists hallucinations and delusions as positive symptoms, names hearing voices as the most common hallucination, and describes withdrawal, flat emotion and loss of interest in self-care as negative symptoms, which can appear months or years before a first acute episode, NHS, symptoms of schizophrenia. ↩
  14. On N-acetylcysteine: a 2020 meta-analysis of seven randomized trials, with 220 people on NAC and 220 on placebo, found that negative and total symptom scores improved after 24 weeks of NAC added to standard treatment, along with working memory. The effects appeared only at the later time point, so short courses are unlikely to show benefit, PubMed 31826654. ↩
  15. On treatment: NHS guidance says antipsychotics can reduce anxiety or aggression within hours but may take days or weeks to reduce hallucinations or delusions, that a first episode should lead to an early intervention team, that another antipsychotic can be tried if one has not helped after several weeks, that most people take medication for 1 or 2 years after a first episode and longer if it recurs, that stopping can bring a relapse, that talking therapies work best combined with medication, and that the care plan should include healthy eating, physical activity and help to stop smoking, NHS, treatment of schizophrenia. ↩
  16. On inflammation: a meta-analysis of 26 studies found C-reactive protein moderately raised in schizophrenia whether or not antipsychotics were taken, rising with positive symptoms and body mass index but unrelated to negative symptoms, PubMed 26169974. ↩
  17. On gut bacteria: a 2021 meta-analysis of 59 case-control studies found a shared pattern across depression, bipolar disorder, schizophrenia and anxiety, with fewer anti-inflammatory butyrate-producing bacteria and more pro-inflammatory ones, and little that was specific to any one diagnosis, PubMed 34524405. ↩
  18. On metabolic syndrome: a meta-analysis of 198 studies with 52,678 people with severe mental illness found metabolic syndrome in 32.6%, a higher risk with every antipsychotic studied than in people never treated, highest with two second-generation drugs and lowest with another, PubMed 26407790. ↩
  19. On homocysteine: a 2026 meta-analysis of 54 case-control studies with 9,781 participants found homocysteine about a third higher on average in schizophrenia, PubMed 42773153, and in a crossover trial of 42 patients with raised homocysteine, 3 months of folic acid, B12 and B6 lowered homocysteine and improved symptom scores compared with placebo, PubMed 16412989. ↩
  20. On probiotics: in a 14-⁠week randomized placebo-controlled trial in 65 outpatients with schizophrenia, a probiotic added to antipsychotic treatment made no significant difference to symptom scores, though fewer people developed severe bowel difficulty. The rehospitalization benefit sometimes quoted comes from a separate trial in people recently hospitalized for mania, not schizophrenia, PubMed 24940526, PubMed 29693757. ↩
  21. On second- versus first-generation antipsychotics: a 2009 meta-analysis of 150 double-blind trials with 21,533 participants found only four second-generation drugs (amisulpride, clozapine, olanzapine and risperidone) more effective overall than first-generation drugs, with small to medium effects. The others were not more effective, even for negative symptoms, and the class varied widely in side effects, PubMed 19058842. ↩
  22. On treatment-resistant illness: pooled trial data found that 40.1% of people with treatment-resistant schizophrenia responded to clozapine, the most effective antipsychotic for the quarter to a third of people whose illness is treatment resistant, PubMed 28655284. ↩
  23. On clozapine: clozapine is the most effective antipsychotic for treatment-resistant schizophrenia and reduces suicidality, and it requires mandatory blood count monitoring because of agranulocytosis risk. It also causes constipation that can become severe and occasionally fatal ileus: a 22-⁠year pharmacovigilance review of serious slow-gut reactions concluded these effects remain inadequately recognized, PubMed 28623627. Its other side effects include sedation, hypersalivation, a risk of myocarditis early in treatment and significant metabolic effects. It is under-prescribed relative to its effectiveness. ↩
  24. On injectable olanzapine: its US prescribing information states that giving intramuscular olanzapine together with a parenteral benzodiazepine is not recommended, because of the potential for excessive sedation and cardiorespiratory depression, FDA prescribing information, olanzapine injection. ↩
  25. On clozapine monitoring: a meta-analysis of 108 studies found severe neutropenia in 0.9% of people prescribed clozapine, with the peak at one month of exposure and negligible levels after one year, PubMed 29786829. The FDA removed the clozapine REMS effective June 13, 2025, and advises that prescribers should continue to monitor ANC according to the prescribing information, FDA, 2025. ↩
  26. On the longer follow-up: the Vienna trial's participants were followed up a median of 6.7 years later, and the authors reported that the brief omega-⁠3 course had lowered both the risk of developing a psychotic disorder and psychiatric illness in general, PubMed 26263244. This was a follow-up of the 81-⁠person trial, whose original result the larger NEURAPRO trial did not replicate. ↩
  27. On fish oil and blood thinners: the US Office of Dietary Supplements notes that fish oil might prolong clotting times in people taking an anticoagulant, although most research finds no significant effect, and that product labeling advises periodic INR monitoring for people taking omega-⁠3 products with anticoagulants, NIH ODS, omega-⁠3 fatty acids. ↩
  28. Gencer B, Djousse L, Al-Ramady OT, Cook NR, Manson JE, Albert CM. Effect of long-term marine omega-⁠3 fatty acids supplementation on the risk of atrial fibrillation in randomized controlled trials of cardiovascular outcomes: a systematic review and meta-analysis. Circulation. 2021;144(25):1981-⁠1990. PubMed 34612056. Seven trials with 81,210 people followed for about 5 years: omega-⁠3 supplements were linked to a higher risk of atrial fibrillation (hazard ratio 1.25), more so in the trials giving higher doses (hazard ratio 1.49), and the risk rose with the dose. ↩
  29. On vitamin D: a meta-analysis of 19 observational studies found lower vitamin D levels in schizophrenia and deficiency in about two-thirds of patients, and called for trials, PubMed 25050991; in an 8-⁠week placebo-controlled trial in 47 clozapine-treated patients with low vitamin D, supplementation raised levels but did not change psychotic, mood or metabolic measures, PubMed 29226809. ↩
  30. On zinc: in a 6-⁠week double-blind trial in 30 inpatients, zinc added to an antipsychotic improved symptom scores more than placebo; patients were not selected for zinc deficiency, and the trial has not been replicated at scale, PubMed 26576178. ↩
  31. On urgent help in the UK: NHS guidance advises calling emergency services or going to an emergency department if someone's life is at risk or you do not feel you can keep yourself or someone else safe, calling 111 for urgent mental health help, and Samaritans on 116 123 at any hour, NHS, urgent help for mental health, NHS, help for suicidal thoughts. ↩
  32. On clozapine warning signs: MedlinePlus advises people taking clozapine to call their doctor immediately for fever, sore throat, chills or other signs of infection, because the medicine can lower white blood cells, and for constipation, nausea, stomach swelling or pain or vomiting, or fever with sweating, confusion, an irregular heartbeat or severe muscle stiffness, MedlinePlus, clozapine. ↩
  33. National Center for Complementary and Integrative Health (NIH), nccih.nih.gov, and the Linus Pauling Institute Micronutrient Information Center, lpi.oregonstate.edu/mic. ↩
  34. Potkin SG, Jin Y, Bunney BG, Costa J, Gulasekaram B. Effect of clozapine and adjunctive high-dose glycine in treatment-resistant schizophrenia. Am J Psychiatry. 1999;156(1):145-⁠147. PubMed 9892314. In 19 people with treatment-resistant schizophrenia on clozapine, adding high-dose glycine for 12 weeks did not reduce positive or negative symptoms, while those on clozapine alone had a 35% fall in positive symptoms, suggesting glycine may interfere with clozapine's effect. ↩
  35. Kleijnen J, Knipschild P. Niacin and vitamin B6 in mental functioning: a review of controlled trials in humans. Biol Psychiatry. 1991;29(9):931-⁠941. PubMed 1828703. A review of 53 controlled trials of niacin, vitamin B6 and multivitamins found serious shortcomings in nearly all of them and no adequate support from controlled trials for vitamin supplementation in schizophrenia. ↩