Inflammation of the pancreas, acute (sudden, severe, often gallstone- or alcohol-related) or chronic (progressive scarring causing exocrine and endocrine insufficiency). Low-fat diet2, alcohol cessation and pancreatic enzymes3 support recovery; antioxidant supplements have not reliably reduced pain6.
Last updated:
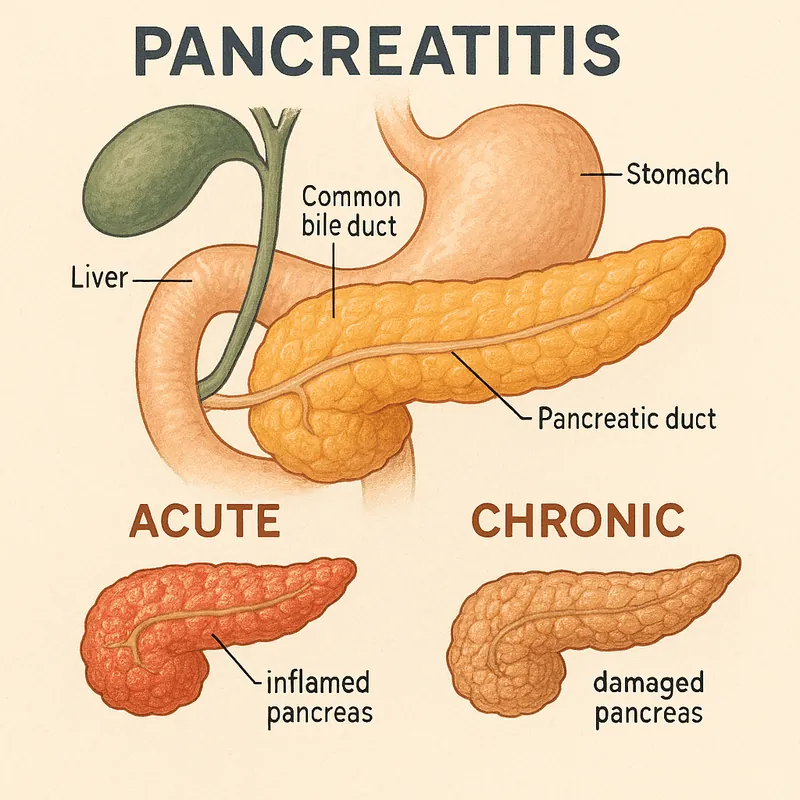
Pancreatitis is inflammation of the pancreas, the organ behind the stomach that produces digestive enzymes (exocrine function) and hormones like insulin and glucagon (endocrine function). When the pancreas becomes inflamed, its enzymes can autodigest the gland itself, causing severe pain, complications and progressive damage.
Acute pancreatitis is a sudden, severe inflammation that can range from mild self-limited to life-threatening with multi-organ failure. More than 80% are caused by gallstones (most common in women)1 or heavy alcohol use (most common in men)13. Chronic pancreatitis is progressive scarring from repeated injury, leading to permanent loss of both digestive and hormonal function (steatorrhea, diabetes).
The pancreas has limited regenerative capacity: once damaged by chronic pancreatitis, it doesn't fully recover. This makes prevention through addressing underlying causes (alcohol cessation, gallstone management, smoking cessation4, lipid control) absolutely critical.
Sudden inflammation, can be mild (interstitial edematous) or severe (necrotizing). More than 80% caused by gallstones or alcohol13. Other causes: hypertriglyceridemia, ERCP, medications, hypercalcemia. Mild cases resolve in days; severe requires ICU.
Pancreatic necrosis, pseudocysts, organ failure (acute); diabetes, exocrine insufficiency, pancreatic cancer (chronic, risk about 8 times higher 5 years after diagnosis, falling with longer follow-up), opioid dependence.
Acute symptoms are unmistakable and severe. Chronic symptoms are more insidious: chronic pain and progressive malabsorption.
| Symptom | What happens |
|---|---|
| Acute Pancreatitis (Emergency) | |
| Severe Epigastric Pain Radiating to Back | Sudden, severe pain in upper abdomen, classically boring through to the back. Often described as "knife-like" or "the worst pain of my life." Relieved (slightly) by leaning forward. Constant, not crampy. |
| Persistent Nausea & Vomiting | Severe nausea with repeated vomiting that doesn't relieve the pain. Inability to keep anything down. Distinguishes from many other GI conditions where vomiting helps. |
| Fever & Tachycardia | Systemic inflammation. Fever may indicate infected necrosis (severe). Rapid heart rate from systemic inflammatory response. Sign of severity needing urgent evaluation. |
| Cullen's & Grey Turner's Signs | Bruising around umbilicus (Cullen's) or flanks (Grey Turner's) indicates severe hemorrhagic pancreatitis with retroperitoneal bleeding. EMERGENCY. Late but ominous signs. |
| Chronic Pancreatitis | |
| Chronic Epigastric Pain | Persistent dull or aching pain, sometimes with acute exacerbations. May worsen with eating (especially fatty foods). Often leads to opioid dependence, a major management challenge. |
| Steatorrhea (Fatty Stools) | Pale, foul-smelling, greasy stools that float. Indicates exocrine insufficiency: the pancreas no longer makes enough digestive enzymes3. Causes fat-soluble vitamin malabsorption (A, D, E, K). |
| Weight Loss & Malnutrition | From malabsorption, pain-induced poor intake and increased metabolic demand. Significant unintentional weight loss is a hallmark of established chronic pancreatitis. |
| New-Onset Diabetes (Type 3c) | Pancreatic damage destroys islet cells, which causes insulin and glucagon deficiency. Causes unstable blood sugar with hypoglycemia common. Different management than type 1 or 2 diabetes. |
Pancreatitis happens when the pancreas becomes inflamed and its own digestive enzymes start damaging the gland12. An acute attack needs urgent hospital treatment, so nothing below is a reason to try a diet or a supplement first; what the causes change is how the next attack is prevented.
| Cause | How It Contributes to Pancreatitis | What Helps |
|---|---|---|
| Gallstones | A gallstone passing through and lodging in a bile or pancreatic duct inflames the pancreas, and this is the most common cause of acute pancreatitis12 | Urgent hospital treatment; then removal of the gallbladder, since having surgery within a few days of admission lowers the chance of complications: it cut recurrent gallstone complications to 5% from 17% in a randomized trial8 |
| Heavy alcohol use | Heavy alcohol use is one of the two most common causes of acute pancreatitis and the most common cause of chronic pancreatitis; continuing to drink after an acute attack leads to more attacks and to chronic pancreatitis, and in alcohol-related chronic pancreatitis it makes severe complications and death more likely12 | Stopping alcohol completely, even if the pancreatitis was mild or early, and even when alcohol was not the cause; ask a clinician for help to stop, and see the diet section |
| Smoking | Smoking makes pancreatitis more likely in the first place, and smoking with acute pancreatitis, especially when alcohol caused it, greatly raises the chance that the pancreatitis becomes chronic; it also raises pancreatic cancer risk124 | Stopping smoking completely, with help from a clinician; the chance of pancreatitis is higher still in people who both smoke and drink alcohol |
| High blood triglycerides | High triglycerides are a recognized cause, generally at levels above about 1,000 mg/dL (11.3 mmol/L), and identifying this matters because it changes how the attack is managed121 | Getting triglycerides measured after an attack; lowering them with the eating pattern in the diet section, with omega-3 as listed in the supplement table and with prescribed lipid-lowering treatment when a clinician advises it |
| Inherited and family factors | Genetic disorders of the pancreas are among the most common causes of chronic pancreatitis, a family history of pancreatitis raises the risk, and so does a personal or family history of gallstones; cystic fibrosis and certain autoimmune conditions also raise it12 | Not modifiable in itself; specialist assessment to find which cause is present, since it changes follow-up, and the alcohol and smoking measures above apply whatever the underlying cause |
| Medicines, procedures, injury and high blood calcium | Some medicines, an injury to the abdomen, a high level of calcium in the blood, an ERCP procedure done to treat something else, an infection and pancreatic cancer are all recognized causes; in many cases no cause is found at all12 | Conventional care: tell the team every medicine and supplement you take, since some medicines are a cause and stopping them is a clinician's decision; new diabetes in an older adult with weight loss and abdominal pain is a reason for prompt specialist assessment5 |
| Test | What it shows |
|---|---|
| Acute Pancreatitis Workup | |
| Lipase & Amylase | Lipase >3x upper normal limit with appropriate symptoms = pancreatitis. Lipase more specific and remains elevated longer than amylase. Cornerstone of diagnosis. |
| CT Abdomen with Contrast | Confirms diagnosis, assesses severity, identifies complications (necrosis, pseudocysts, vascular involvement). Best timing: 72+ hours after onset to assess necrosis. Not always needed if clinical/lab diagnosis clear. |
| Severity Markers & Risk Stratification | Blood tests and scoring systems that predict how severe the attack will be. Identifies severe cases needing intensive care. |
| Chronic Pancreatitis & Etiology Workup | |
| MRCP / EUS | Magnetic Resonance Cholangiopancreatography or Endoscopic Ultrasound for chronic pancreatitis diagnosis. Shows ductal changes, calcifications, atrophy. EUS most sensitive for early disease. |
| Fecal Elastase | Marker of exocrine pancreatic function. <200 mcg/g suggests insufficiency; <100 mcg/g severe. Used to diagnose exocrine pancreatic insufficiency (EPI) and titrate enzyme replacement. |
| Etiology Investigations | Triglycerides (hypertriglyceridemia), calcium (hyperparathyroidism), genetic testing (PRSS1, SPINK1, CFTR, CASR), IgG4 (autoimmune pancreatitis). Address underlying cause. |
| Diabetes & Nutritional Workup | HbA1c, fasting glucose, OGTT for diabetes screening. Fat-soluble vitamins (A, D, E, K), B12, magnesium, zinc, all commonly deficient in chronic pancreatitis from malabsorption. |
Cause elimination (alcohol, gallstones, triglycerides), low-fat diet during recovery, enzyme replacement
Diet varies by phase. Acute: early oral feeding as tolerated; a low-fat solid diet can be the first meal, without clear liquids first2. Recovery: gradual reintroduction. Chronic: small frequent meals, enzyme replacement with meals and no severe fat restriction.
What to eat in pancreatitis recovery, and what to strictly avoid
| What to eat or do | Details |
|---|---|
| โ Prioritize These: | |
| Lean Proteins | Skinless chicken, egg whites, low-fat dairy if tolerated. Important during recovery and for preventing protein-calorie malnutrition. |
| Cooked Vegetables & Fruits | Easy to digest, nutrient-rich. Steamed, baked or pureed. Avoid raw during flares. Antioxidant-rich, though antioxidant supplements have not reduced pain in randomized trials. |
| Whole Grains (Refined During Flares) | Brown rice, oatmeal, quinoa during stable times. White rice, plain pasta during acute recovery. Easy energy source. |
| MCT Oil (Medium-Chain Triglycerides) | MCTs absorb without pancreatic enzymes, useful in chronic pancreatitis with exocrine insufficiency. Provides calories when fat malabsorption is severe. |
| โ Strictly Avoid: | |
| All Alcohol | No alcohol, whatever the cause. Stopping alcohol is the most important dietary step4. |
| High-Fat & Fried Foods | Fried foods, fatty meats, full-fat dairy, butter-heavy dishes. Fat stimulates pancreatic enzyme secretion, which can bring on pain. During recovery from an acute attack, keep fat to about 25 to 30% of calories; in chronic pancreatitis, eat normal amounts of fat with your enzymes and avoid fried foods. |
| Refined Sugar & Carbs | Sweets, pastries, sodas. Stress already-compromised insulin secretion. Worsen blood sugar control in pancreatogenic diabetes. Replace with whole-food carbohydrates. |
| Smoking | Independent risk factor for chronic pancreatitis progression and pancreatic cancer. Quit completely, most impactful long-term intervention besides alcohol cessation. |
Some of these supplements replace malabsorbed nutrients or support digestion; where trials found no benefit, the row says so.
| Supplement | What it is for | Typical range | Timing | Notes & cautions |
|---|---|---|---|---|
| Pancreatic Enzymes (PERT) | Replace deficient pancreatic enzymes (amylase, protease, lipase). Essential when exocrine insufficiency present. Improves digestion and nutrition; in trials it did not relieve pain17. | 40,000 to 80,000 lipase units per main meal; half with snacks | With each meal/snack | Prescription enzyme products are standardized. Take with the first bite of a meal. Adjust to symptoms and fecal elastase. |
| Antioxidant Combination | Selenium + methionine + ascorbic acid + beta-carotene + vitamin E. Results are mixed6, and the ANTICIPATE randomized trial found no reduction in pain compared with placebo10. The beta-carotene is a concern for anyone who smokes, because beta-carotene supplements increased lung cancer in smokers in large trials (see the lung cancer guide). | Not recommended for pancreatitis pain (trials found no benefit over placebo) | Not applicable | Discuss with your specialist before starting. |
| Fat-Soluble Vitamins (A, D, E, K) | Commonly deficient in chronic pancreatitis with exocrine insufficiency3. Replete based on serum levels. Vitamin D particularly important. | Per blood tests | With fat meal + enzymes | Test annually. Vitamin K often forgotten, important for bone health and clotting. If you take warfarin, clear any vitamin K supplement with the clinician managing your anticoagulation before starting or stopping it: vitamin K antagonizes warfarin, and changing your intake destabilizes the INR. Consistency matters more than avoidance. This does not apply in the same way to direct oral anticoagulants such as apixaban or rivaroxaban, but tell your prescriber about any supplement you take. |
| Vitamin B12 | Frequently deficient. Pancreatic enzymes are required for B12 absorption (cleave R-binder). Often need supplementation. | 1,000 mcg sublingual/day | Any time | Test serum B12 and methylmalonic acid. |
| Curcumin (Turmeric) | Anti-inflammatory. In a small randomized trial in chronic pancreatitis it did not improve pain18. Limited evidence. | Not recommended for pancreatitis pain (the pilot trial used 500 mg with piperine) | Not applicable | Avoid with bleeding disorders. Liver damage has been reported with high-absorption curcumin products; stop and talk to your clinician if you notice fatigue, nausea, poor appetite, dark urine or yellowing of the skin or eyes19. |
| Omega-3 EPA/DHA | Anti-inflammatory; useful particularly in hypertriglyceridemia-induced pancreatitis (lowers triglycerides). | 2 to 4 g/day combined EPA+DHA | With fat meal + enzymes | Prescription omega-3 products (icosapent ethyl, omega-3-acid ethyl esters) for severe hypertriglyceridemia. Third-party tested. If you take an anticoagulant, tell the clinician managing it before starting, as high doses can affect clotting and periodic INR checks are advised20. In heart trials, fish oil supplements raised the risk of atrial fibrillation, an irregular heartbeat, more so above 1 g a day22, so check this dose with your clinician first. |
| Magnesium & Zinc | Both frequently deficient from malabsorption. Support pancreatic function and enzyme activity. | Mg: 300 to 400 mg glycinate; Zn: 15 to 30 mg. | Magnesium evening; zinc with meal (not with iron) | Test magnesium (serum is the standard test). Take magnesium well apart from antibiotics and osteoporosis medicines, whose absorption it can reduce, and check with a clinician first if you have reduced kidney function21. Excess zinc >30 mg long-term can cause copper deficiency. The top of this range is above the 350 mg/day upper intake level for supplemental magnesium; above that, diarrhea is common. |
| Probiotics | Sometimes used for diarrhea; evidence in chronic pancreatitis is limited. | Multi-strain 25 to 50 billion CFU | With meals | If a product contains S. boulardii, note that it is a yeast rather than a bacterium. Avoid in acute severe pancreatitis: in a randomized trial, probiotics given to people with predicted severe disease increased deaths11. Use caution with immunosuppression or a central line, as yeast bloodstream infections have been reported; discuss with your team. |
Acute pancreatitis is treated in the hospital; this covers recovery and preventing recurrence.
Hospital care comes first. Most people start getting better within a week and leave the hospital in 5 to 10 days, longer with severe disease. Eating restarts as tolerated rather than waiting for pain to go; a low-fat solid diet is a reasonable first meal2.
Most people recover fully. Repeated attacks lead to chronic pancreatitis, so the cause is dealt with, not waited out. Pale, greasy, foul-smelling stools or weight loss point to too little digestive enzyme; a stool test measures it, and prescribed enzyme replacement with meals is the treatment3.
The gland does not fully recover, so the work is replacement: enzymes with meals, checks on vitamins A, D, E and K, and diabetes screening. Severe fat restriction backfires, worsening energy intake and vitamin absorption3.
Call 911 or go to the emergency department for sudden severe upper abdominal pain spreading to your back, with a fast heartbeat, difficulty breathing or bloating that does not settle; if the skin around the navel, waist or upper outer thigh looks blue or bruised; or for yellow skin or eyes with a fever. Get care right away for severe or worsening abdominal pain, nausea and vomiting, fever or chills, shortness of breath or yellow skin or eyes. Do not try a diet, a fast or a supplement first: untreated, these problems can be fatal.
Get new guides in your inbox. Once a month: new condition guides and research updates, including the trials that did not work. Free, no spam, and you can unsubscribe in one click.
Once scarred by chronic pancreatitis, the pancreas does not fully recover. Prevention is everything: eliminate alcohol, manage gallstones, control triglycerides, quit smoking. Combined with enzyme replacement, quality of life can improve considerably; antioxidant supplements did not reduce pain in a randomized trial.
Each numbered entry below is either a source you can follow or a note setting out what the evidence does and does not support. Both are numbered together so the markers in the text line up.
Last reviewed October 20, 2026. Supplement entries are cross-checked against the NIH National Center for Complementary and Integrative Health and the Linus Pauling Institute Micronutrient Information Center.7 Acute pancreatitis is a medical emergency. Severe upper abdominal pain radiating through to the back, often with vomiting, needs an emergency department, not a dietary change. Two things about this condition are commonly gotten wrong. Prolonged fasting with nothing by mouth is outdated: current guidance is early oral or enteral feeding as tolerated, because it preserves the gut barrier and improves outcomes, and the old practice of resting the pancreas for days has been abandoned. And in chronic pancreatitis, fat restriction is not the answer: pancreatic enzyme replacement taken with meals is, because restricting fat without enzymes causes weight loss and fat-soluble vitamin deficiency. Alcohol and smoking cessation do more than any supplement here.